

When I see a recurring rash in the clinic, there is one thing patients almost always say first: "I guess my immunity has dropped lately." When an itchy rash flares up during a period of fatigue, built-up stress or lack of sleep, it is natural to assume it is because your immunity has broken down.
In fact, if you search for "immunity" on Naver, you will find endless stories about boosting immunity or things that are good for immunity. That is how hot a topic it is. In the clinic, however, I often find myself saying something a little different. That is because, not infrequently, a rash that people believe was caused by low immunity is treated by lowering the immune response instead.
For a rash blamed on low immunity, why use a medicine that lowers immunity?
A mild rash usually settles down after taking medication for a few days or applying an ointment. The problem is when the rash keeps recurring in the same spot. In such cases many people worry, "Is it because my immunity is down?", yet the medicine actually prescribed is often a steroid, which suppresses the immune response.
If the problem came from low immunity, it would seem that immunity should be boosted, so it sounds ironic that the treatment goes in the opposite direction. To resolve this contradiction, we need to take another look at the word "immunity power" itself.

In fact, "immunity power" is not a medical term
Strictly speaking, the expression "immunity power" (myeonyeongnyeok in Korean) that we commonly use is not in the dictionary. The precise term used in medicine is simply immunity.
Immunity is the body's defense system against antigens such as bacteria, fungi and viruses that enter from outside the body and cause disease. It is easy to understand if you compare it to an army that keeps outside enemies from invading.
When this line of defense weakens, the body naturally becomes vulnerable to invaders. Representative conditions that tend to occur when immunity is low include the following.
- Impetigo
- The common cold
- Fungal infections (tinea corporis, tinea pedis, tinea cruris, etc.)
- Herpes simplex
- Shingles
As you can see, most of these arise from infection. In other words, the diseases caused by low immunity are closer to infectious diseases caused by germs invading from outside.
Then is an itchy rash also caused by low immunity?
This is the point many people are most curious about. Are common skin rashes such as atopic dermatitis, seborrheic dermatitis and contact dermatitis also caused by low immunity?
To give you the conclusion first, no. In these conditions, immunity itself has not weakened; rather, something has gone wrong with the ability to regulate immunity appropriately, so the immune response in a specific area rises excessively. The direction is exactly the opposite of infectious diseases.
Summarizing the two branches in a table looks like this.
| Category | Representative conditions | State of immunity | Direction of treatment |
|---|---|---|---|
| Infectious diseases | Impetigo, fungal infections, herpes simplex, shingles | Defenses weakened | Eliminate the causative organism, restore defenses |
| Inflammatory skin diseases | Contact dermatitis, atopic dermatitis, seborrheic dermatitis | Local immune response excessive | Suppress the excessive immune response |
Let me use contact dermatitis as an example.
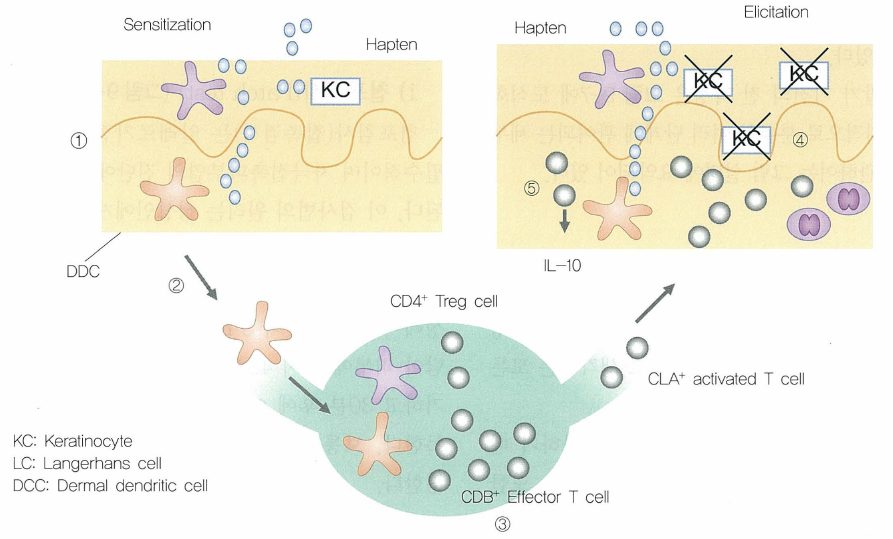
Allergic contact dermatitis is a phenomenon in which the body recognizes an external substance, such as metal or hair dye, as harmful and mounts an excessive immune response against it, ending up damaging its own skin. Treatment therefore proceeds in the direction of calming this excessive immune response. This is exactly why medicines that lower immunity are used for a recurring rash.
I have covered in a little more detail how I read facial dermatitis with repeated redness and inflammation like this in Facial redness and rosacea, which I often see in the clinic.
A rash caused by low immunity and a rash caused by disrupted immune regulation may look similar on the surface, but the direction of treatment can be exactly the opposite.
If it is hard to judge on your own whether a recurring rash is due to infection or a problem of regulation, you can start by sharing the pattern of your symptoms through Consult via chat now.
Why I recommend "rest" first for atopic dermatitis and seborrheic dermatitis
For atopic dermatitis, seborrheic dermatitis and many other types of dermatitis, I tend to emphasize "rest" before medication. In many cases, symptoms ease noticeably just by sleeping well, eating well and reducing stress.
This is because stress interferes with the recovery of the skin barrier and fuels the inflammatory response. I have summarized lifestyle habits that rebuild a broken barrier in Lifestyle habits that restore the skin barrier, like rebuilding a collapsed castle wall, so it may be helpful to refer to it as well.
There are also some things worth trying in daily life.
- Drink plenty of water, frequently
- If you have atopic dermatitis, try taking evening primrose oil or similar as a supplement
- Help the skin barrier recover by managing sleep and stress
I continue explaining the criteria for choosing a moisturizer when itching and dryness keep recurring in Why I recommend urea before a new moisturizer for winter itch.
In the end, a rash cannot be explained by a single cause
Here is what I wanted to say today: so many factors are intertwined in a skin rash that it is hard to simply declare, "the rash appeared because my immunity dropped."

Just as you cannot divide everyone in the world into only the good, the bad and the weird, a rash cannot be explained along the single axis of high or low immunity. The direction of treatment differs completely depending on whether it comes from infection or from a local reaction that has become excessive because regulation is disrupted. If a rash keeps coming back in the same spot, distinguishing the cause is the first step.
If you are also concerned about pigmentation left after the inflammation subsides, I recommend taking a look at Why early care matters for post-inflammatory hyperpigmentation as well. If your symptoms are unclear, feel free to reach out via Consult via chat.
References
- Kang, Sewon. Fitzpatrick's Dermatology. McGraw Hill Professional, 2018.
- Dermatology, 6th ed. The Korean Dermatological Association.
Author: Dr. Cho Mingyeol, Medical Director (board-certified dermatologist; Master Certification in Pigmentation, Acne, Rosacea and Hair from the Korean Dermatologists Association). You can find the full profile on the Medical Team page. First published 2021-08-04 / Last reviewed 2026-07-09
This article is intended for general information only; the appropriate treatment and outcomes may vary depending on each individual's condition.